When execution becomes the constraint
The industry has never had better tools for identifying problems. Over the last decade, heavy investment in real-time dashboards, risk-based monitoring, and centralized data review has transformed visibility. Teams can now spot risks with more precision than any previous generation.
Clinical trial execution becomes a constraint when timelines still slip, protocol deviations are repeated, and trial costs compound. The failure isn't a lack of data; it is a structural breakdown in how that data is converted into coordinated, timely action. We have mastered detection, but the system of execution remains broken.
Getz and Kaitin characterize this as a third translational barrier in drug development — distinct from scientific gaps, and more operationally damaging than either. Read the full Tufts CSDD perspective: Recognizing and Addressing the Execution Translation Gap in Clinical Trials. It is not a knowledge problem. It is a clinical trial execution problem.
Why manual coordination cannot scale — and how it breaks
Manual coordination cannot scale clinical trials because every additional study demands a proportionate increase in headcount to manage it, driving up trial operating cost. In the past, coordination relied on follow-up calls, endless email chains, and informal escalations. But as protocol complexity grows and site networks expand, the human bandwidth required to hold cross-functional execution together now exceeds what any team can sustain. This isn't a process failure; it is a capacity failure.

Reason 1: Instructions don't reach sites consistently
In a manual coordination model, a corrective decision made at the sponsor level has to travel through a CRO layer and then down to individual sites, each with their own local teams, timelines, and interpretations. There is no governed mechanism to ensure the decision arrives, is understood, and is acted upon uniformly.
- The same protocol amendment gets implemented differently across sites.
- A corrective action applied at one site never reaches another.
- Instructions are acknowledged but not followed through, because nothing in the system verifies that they were.
Reason 2: A single delay cascades across the study
Clinical trial workflows are sequentially dependent. When one handoff breaks, the downstream impact compounds before anyone catches it.
- A delayed amendment stalls site activation until implementation is complete.
- A stalled data query pushes database lock and delays submission readiness.
- A slow vendor reconciliation extends the study timeline for everyone downstream.
By the time the delay appears in a status report, recovery is already expensive and rarely brings the study back on schedule.
Reason 3: There is no system to confirm that actions were actually taken
Manual coordination lacks an execution memory. An email is sent, a phone call is made, a corrective action is recorded — but was it done in the right place, at the right time, in the right way? Those questions often remain unasked.
- Interventions are initiated but not sustained.
- Issues resolved at one site reappear at another.
- The loop is never closed, because no system was built to close it.
Why current approaches cannot close the execution gap
Despite advances in analytics, monitoring, and point automation, the execution gap persists. The reason is structural.
- Analytics platforms detect issues but do not resolve them.
- Dashboards visualize risk but do not trigger coordinated action.
- Point AI tools automate tasks but do not manage cross-functional dependencies.
Execution remains dependent on manual coordination — emails, follow-ups, and local ownership. As a result, the system can see problems clearly but cannot act on them consistently. This is why the execution gap continues to impact cost, timelines, and compliance despite better visibility. For the underlying operating model, see our complete guide to AI agents in clinical trials.
Why the execution gap is a cost problem
Even when progress stalls, trials continue to run, resources remain engaged, and inefficiencies accumulate across functions. Over time, this shifts cost from planned to uncontrolled.
The financial reality
The cost of a Phase III trial is estimated at $56,000 per day, and that burn continues to accrue even when the process is delayed. As Kenneth Getz and Kenneth Kaitin note in Applied Clinical Trials, a 90-day delay alone can add $5M+ in direct costs, excluding internal overhead.
How existing systems fuel hidden costs
Analytics platforms surface warning signs, traditional systems scale linearly with headcount, and point AI solutions handle siloed processes. What each lacks is the action layer needed to stop cost compounding. Hidden costs build when Execution Risk Indicators (ERIs) — the metrics that signal operational friction — are detected but not resolved.
- Observation vs. orchestration: CTMS and dashboards track what has happened; they do not orchestrate what needs to happen next, leaving gaps to be closed through manual follow-up.
- The detection tax: identifying a cost driver and resolving it are two different things. Without automated coordination, flagging an ERI simply creates a larger backlog of manual tasks that overstretched teams cannot sustain.
- The loop-closing failure: when interventions aren't triggered automatically across vendors, recurring deviations turn into compounding financial burdens. A single oversight becomes a multi-million-dollar delay because the system couldn't close the loop.
| Execution failure | Direct cost driver | Compounding effect |
|---|---|---|
| 90-day delay | $56K/day × 90 = $5M+ | Deferred revenue; portfolio-level impact |
| Amendment backlog | Site holds on affected workflows | Enrollment delay; start-up extension |
| Site underperformance | Backup site activation costs | Overall study duration increase |
| Deviation rework | Monitoring escalation; additional oversight | Resource drain; audit burden |
| Slow database lock | Vendor reconciliation overhead | Delayed submission readiness |
Why the execution gap is a timeline problem
The execution gap becomes a timeline problem because current systems are designed to monitor what has happened, not to coordinate what needs to happen next. As a result, delays are not only frequent — they become unpredictable, driven by unsynchronized workflows, slow handoffs, and inconsistent execution across stakeholders.
The reality in numbers
Research from Tufts CSDD, published in Applied Clinical Trials, confirms a systemic slowdown:
- Start-up cycles: protocol approval to FPFV has extended by 30–45% since 2015.
- Amendment lag: implementation now averages 260 days — a 154% increase since 2010.
- Deviation volume: Phase III deviations have risen 56% in five years, from 189 to 296.
How existing systems delay timelines
While visibility has improved, legacy systems remain passive repositories. They record that a milestone was missed, but they lack the AI-enabled execution layer required to prevent the miss.
- Record vs. action: the CTMS documents events that have occurred rather than actions that need to be taken, so the response still depends on a human noticing the warning sign.
- The point solution gap: many AI tools automate isolated tasks but offer no end-to-end accountability, leaving time-sensitive transitions to manual follow-up.
- The cascade effect: because legacy tools cannot trigger proactive responses, a single bottleneck quickly compounds into a trial-wide slip — a framework failure that human teams cannot out-staff.
Related reading on earlier, targeted signal detection: AI-enabled risk-based monitoring.
Why the execution gap is a compliance problem
The execution gap becomes a compliance problem when corrective actions are not consistently applied across sites, leading to recurring deviations, fragmented audit trails, and variation in protocol adherence. Compliance frameworks define what should happen; execution determines whether it actually happens.
The data
- Deviation surge: Phase III deviations rose 56% in five years — not because monitoring failed, but because the response to monitoring didn't produce lasting change.
- The SDV trap: despite widespread RBQM adoption, many teams still perform 100% source data verification, contradicting the model's intent.
This represents strategic intent without operational follow-through, creating a measurable compliance risk that legacy systems cannot mitigate.
How existing systems compromise compliance
Inconsistent execution creates protocol variation across sites — and that variation is exactly what regulators are trained to identify.
- Systemic failure vs. one-off fixes: recurring deviation patterns signal that root causes aren't being addressed systemically. Analytics platforms may see the pattern, but they lack the governed action layer required to stop it.
- Audit trail fragmentation: relying on emails and calls creates fragmented audit trails, making it nearly impossible to demonstrate a clear chronological history of when and how corrective actions were taken during a submission review.
- Credibility gaps: when RBQM claims don't match actual monitoring behavior, the credibility of the entire quality system is undermined. Without an orchestration layer, the risk-based approach exists only on paper.
From execution gaps to execution systems
Understanding the gap is only the first step. Closing it requires a shift in how execution itself is structured, moving from manual coordination to system-driven execution.
Most trials still rely on reactive, manual responses to data alerts. At today's volume and protocol burden, the industry needs a supervised execution layer that works alongside human teams to perform defined workflows. This model — an AI Workforce for clinical trials — is designed to maintain cross-functional coordination and produce governed action, ensuring that detection actually leads to resolution.
How the AI Workforce model operates
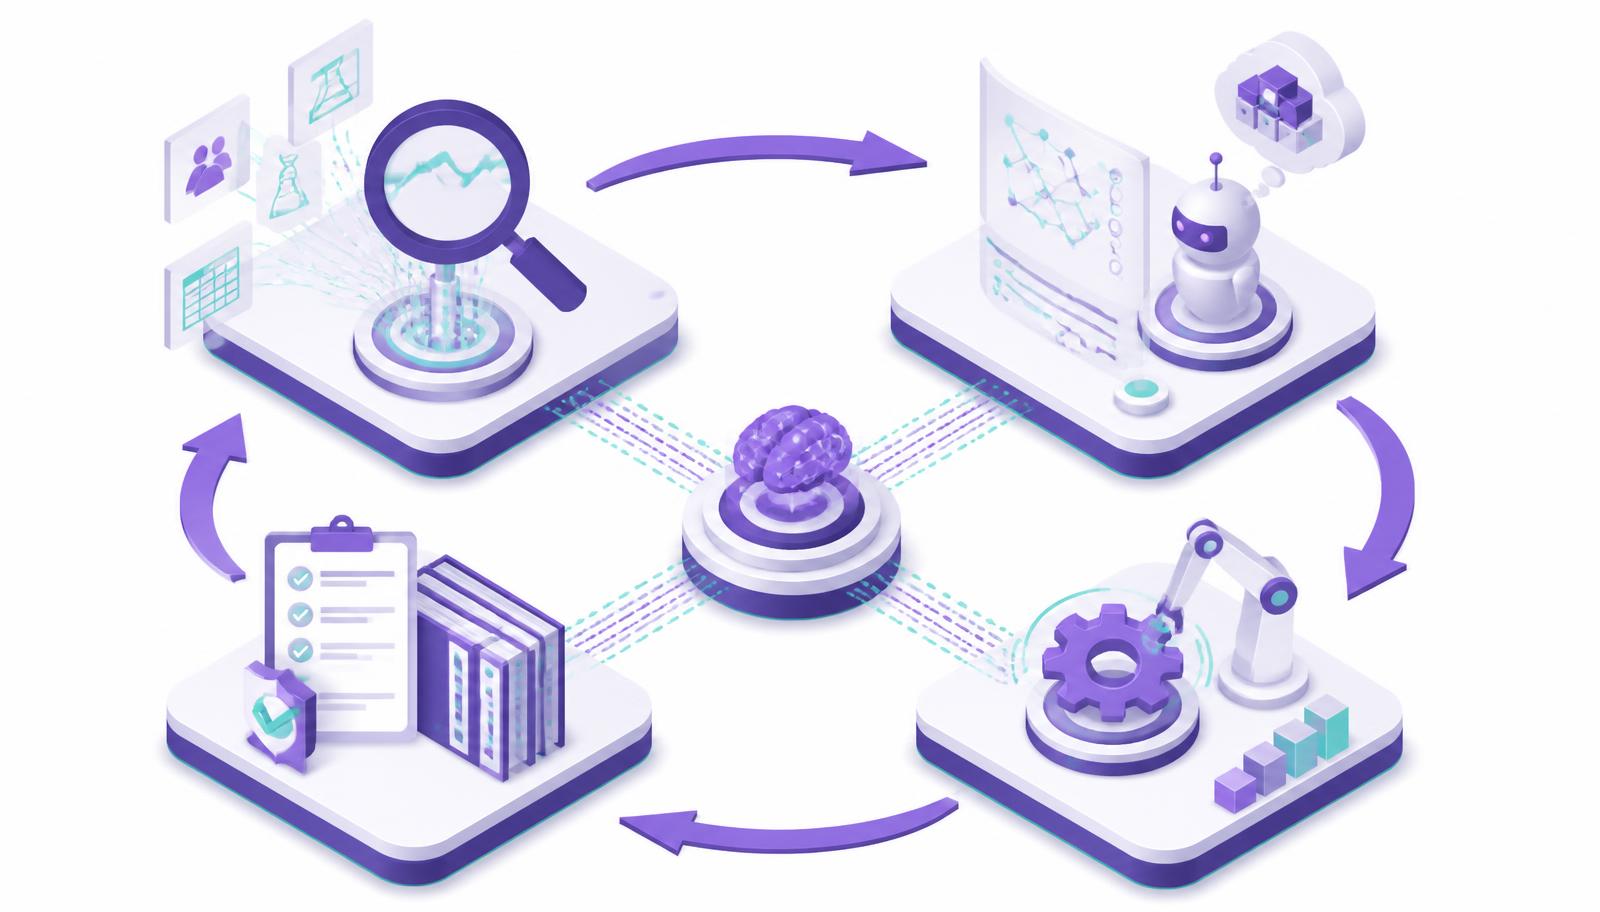
In practice, this model operates through a structured execution layer that works alongside human teams, ensuring that identified issues are translated into coordinated action across the trial ecosystem. An AI Workforce does not replace human expertise; it orchestrates execution across systems while experts supervise, validate, and intervene where required.

- Converts signals into governed action paths: when a deviation threshold is crossed or a site falls behind, the issue is routed to the correct cross-functional owners with defined response protocols and timelines — moving from a passive alert to governed action.
- Orchestrates across functional silos: unlike point AI tools that automate discrete tasks, the AI Workforce maintains execution continuity at the sponsor–CRO–site handoff points, where delays most often occur.
- Proactively operationalizes Execution Risk Indicators (ERIs): by setting thresholds for amendment timelines and data reconciliation, the model triggers supervised execution the moment an ERI is flagged.
- Scales throughput without proportional headcount: by performing structured, repeatable workflows such as data query resolution and enrollment coordination, capacity grows without linear resource expansion.
This is the type of operating layer now emerging in clinical trials. The Maxis AI platform is built on this model — an AI Workforce designed to enable governed execution across complex, regulated workflows.
Regulatory frameworks reinforce this direction. ICH E6(R3) emphasizes proactive risk management and sponsor oversight, ICH E8(R1) ties execution to critical-to-quality design, and the FDA's December 2024 draft guidance on protocol deviations calls for structured root cause analysis and systemic learning — exactly what governed execution delivers.
Conclusion: closing the gap
Clinical trials are no longer constrained by how effectively they can detect issues, but by how reliably they can act on them. The recurring challenges in cost, timelines, and compliance all point to the same structural limitation — execution has not scaled with complexity.
Closing this gap requires more than incremental improvement. It represents a shift from manual, coordination-driven models to system-driven execution. Organizations that make this shift will not only improve operational efficiency, but also gain stronger control over timelines, costs, and regulatory outcomes. This is not an optimization. It is a change in how clinical trials are executed.
Continue the series
This pillar guide is supported by three deep-dives: Clinical Trial Execution Gap: From Risk Signals to Action covers governed action paths and Execution Risk Indicators; What Is a Clinical Trial Execution System? defines the systems-of-action category and how to evaluate one; and Clinical Trial Operations Automation: A 3-Stage Maturity Model maps the path from point automation to supervised orchestration.
Frequently asked questions
What is the execution gap in clinical trials?
Why can't manual coordination in clinical trials scale with modern protocol complexity?
How does an AI Workforce differ from CTMS or analytics tools?
How do Execution Risk Indicators (ERIs) improve trial outcomes?
Does an AI Workforce replace the human role?
References
Sources & references
- Recognizing and Addressing the Execution Translation Gap in Clinical Trials (2026) — Getz, K., & Kaitin, K.I., Applied Clinical Trials
- ICH E6(R3): Guideline for Good Clinical Practice — International Council for Harmonisation
- ICH E8(R1): General Considerations for Clinical Studies — International Council for Harmonisation
- Draft Guidance: Protocol Deviations in Clinical Investigations (December 2024) — U.S. Food and Drug Administration

About the author
Dr. Anika Rao
Head of Clinical AI, Maxis AI
Anika leads Maxis AI's clinical agent practice, working with sponsors and CROs on governed deployments across CDM, biometrics, and oversight.